What are cancer biomarkers? Classes, measurement and validity
By OncoFirm Diagnostics · Last updated October 2026
Cancer biomarkers are measurable characteristics, usually molecules or cells in tissue, blood or other body fluids, that carry information about a cancer: whether it is likely to be present, how it may behave, or how it is responding to treatment. A biomarker is not a diagnosis; each one answers a narrow question, and only as well as the evidence behind it allows.
This guide sorts biomarkers by what they are used for and what they are made of, then sets out the two tests every candidate must pass before it can sit inside a diagnostic: analytical validity and clinical validity. It is written for researchers deciding where a marker, an assay or a cohort might fit in a study.
Intended use comes before chemistry
The FDA-NIH BEST glossary classifies biomarkers by purpose: susceptibility or risk, diagnostic, monitoring, prognostic, predictive, pharmacodynamic or response, and safety. A prognostic marker informs the likely course of disease whatever the treatment; a predictive marker identifies who is likely to benefit from a specific therapy.
One molecule can perform well in one role and poorly in another. Serum tumor markers in routine use earn their place mainly in monitoring treatment and in surveillance after surgery, and few are suitable for screening people without symptoms (Duffy, 2013). Whether finding cancer sooner changes outcomes at all is a separate question, covered in why early cancer detection matters and where its limits lie.
Five classes of cancer biomarker
Molecular type largely determines the specimen and the measurement technology.
Protein
Secreted or shed proteins and glycoproteins such as CEA, CA-125, PSA and AFP. Measured mostly by immunoassay. Most are also produced by normal or inflamed tissue.
Genetic
Inherited variants such as BRCA1 and BRCA2 that indicate risk, and somatic alterations in genes such as EGFR, KRAS and BRAF that guide therapy. DNA methylation patterns are often grouped alongside.
RNA
Messenger RNA expression signatures and microRNAs. Multigene expression assays on tumor tissue inform prognosis in some breast cancers; circulating RNA markers remain largely investigational.
Cellular
Circulating tumor cells, and features of the immune infiltrate such as tumor-infiltrating lymphocytes, assessed by cytometry, imaging or pathology.
Metabolic
Small molecules that reflect altered tumor metabolism, profiled by mass spectrometry or nuclear magnetic resonance. Few have reached routine use as blood tests in oncology.
How cancer biomarkers are measured
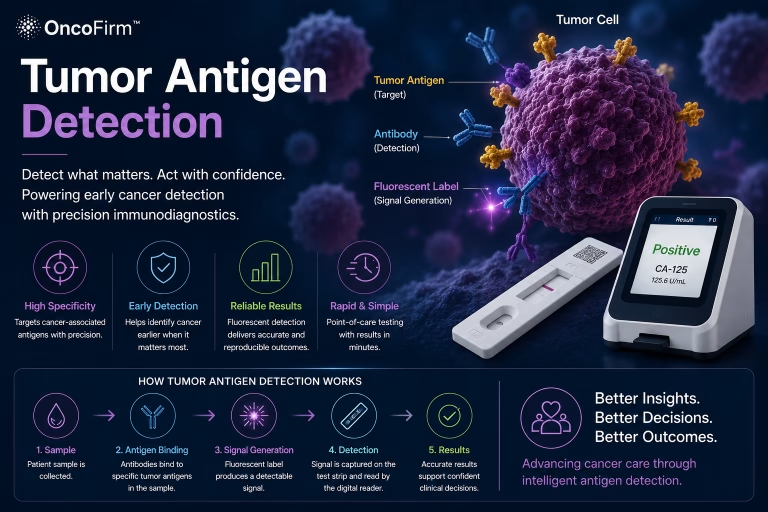
Each class has its own toolkit. Proteins are measured mostly by immunoassay, in which antibodies capture and label the target; formats range from automated laboratory analyzers to the strip tests described in how lateral flow assays work.
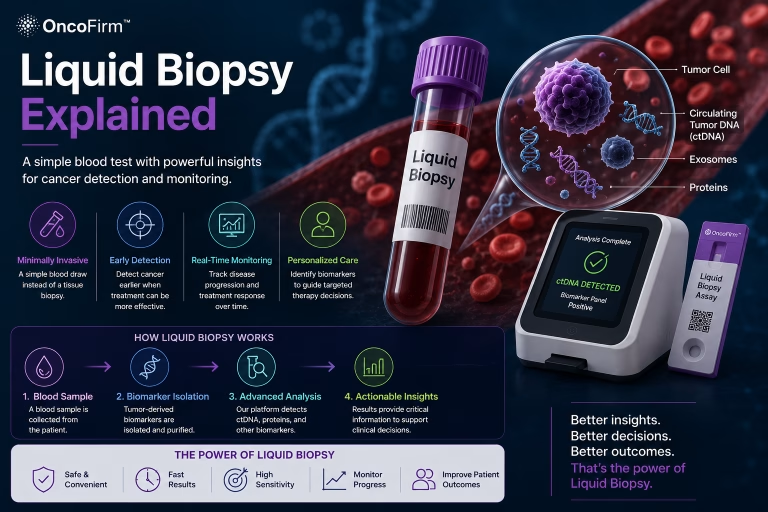
DNA and RNA are measured by PCR, digital PCR and sequencing, on tissue or on the fragments that circulate in plasma. The blood-based versions are covered in liquid biopsy explained. Cells are counted and characterized by flow cytometry, imaging and immunohistochemistry.
Whatever the method, the result depends on steps taken before the instrument: specimen type, collection tube, time to processing and storage. Differences in that handling are a recognized reason a marker that separated groups in one study fails in the next.
Where protein biomarkers sit in biochemical diagnostics
Biochemical diagnostics, usually called clinical chemistry, is the branch of laboratory medicine that measures chemical constituents of body fluids: electrolytes, metabolites, enzymes, hormones and proteins. Tumor marker measurement is one corner of that discipline, run mostly by immunoassay on the same automated analyzers as hormone and cardiac protein tests.
The connection matters because clinical chemistry has mature conventions for calibration, reference intervals, internal quality control and external quality assessment. A new protein assay is judged against them, and one raised value is read in clinical context, never as a diagnosis.
Analytical validity and clinical validity
Analytical validity asks whether the assay measures the analyte correctly: precision, limit of detection, linearity, interference, stability and agreement with a reference method. Clinical validity asks whether the result separates people with and without the condition in the population the test is meant for, expressed as sensitivity, specificity and predictive values. Clinical utility, a third and harder standard, asks whether acting on the result improves outcomes.
Candidates usually stall between the first and second. Discovery studies often compare patients with advanced cancer against healthy volunteers, which flatters a marker that will later face early-stage disease and benign conditions that raise the same protein (Crosby et al., 2022).
Tumors are also biologically diverse, so one marker rarely covers a whole cancer type (Duffy, 2013). That is the argument for studying panels, discussed in tumor antigen detection, and for combining analyte classes in one test (Cohen et al., 2018).
Open questions for research collaborators
OncoFirm™ is a research-and-development-stage company developing a fluorescent lateral flow immunoassay platform for cancer-associated protein biomarkers; its performance has not been established. The open questions are the ones above: which protein markers hold up in intended-use populations, how specimen handling affects them, and which reference methods a strip-based measurement should be compared against.
Biobank holders, clinical chemists and biostatisticians are the natural partners for that work. Current topics are listed under research and development priorities, and proposals can be raised through the research collaboration inquiry.
Frequently asked questions
What is a cancer biomarker in simple terms?
A measurable characteristic, such as a protein in blood or a mutation in tumor DNA, that gives information about a cancer. Depending on the marker, that information may concern risk, presence, likely course or response to treatment.
Can a biomarker test diagnose cancer on its own?
In most cases, no. Diagnosis of a solid tumor generally rests on imaging and tissue pathology, and biomarker results add information to that workup.
What is the difference between a prognostic and a predictive biomarker?
A prognostic biomarker indicates the likely course of disease whatever the treatment. A predictive biomarker identifies patients more likely to respond to a particular therapy, as an EGFR mutation does for EGFR inhibitors in lung cancer.
Why do so few candidate biomarkers reach clinical use?
Most fail validation: results from small case-control studies do not hold in independent, intended-use populations, or the assay cannot be reproduced across laboratories. Showing that use of the marker improves patient outcomes is a further hurdle.
Related research and resources
- Tumor antigen detection — antigen classes, single-marker specificity and how panels are studied
- Liquid biopsy explained — circulating DNA, cells, vesicles and proteins, and their limits in early disease
- How lateral flow assays work — the strip format used for near-patient protein measurement
- Research and development priorities — the questions OncoFirm is seeking partners to work on
References and further reading
- FDA-NIH Biomarker Working Group. BEST (Biomarkers, EndpointS, and other Tools) Resource. Silver Spring (MD): U.S. Food and Drug Administration; Bethesda (MD): National Institutes of Health.
- Duffy MJ. Tumor markers in clinical practice: a review focusing on common solid cancers. Med Princ Pract. 2013;22(1):4–11.
- Crosby D, Bhatia S, Brindle KM, et al. Early detection of cancer. Science. 2022;375(6586):eaay9040.
- Cohen JD, Li L, Wang Y, et al. Detection and localization of surgically resectable cancers with a multi-analyte blood test. Science. 2018;359(6378):926–930.
Research and regulatory status
OncoFirm™ technologies described on this site are in research and development. Their performance characteristics have not been established, and no OncoFirm product has been cleared, approved or authorized by the U.S. Food and Drug Administration. Nothing here is medical advice. Reference to a federal agency or funding program does not imply endorsement, funding, sponsorship or affiliation.