Laboratory information system integration for point-of-care readers
By OncoFirm Diagnostics · Last updated October 2026
Laboratory information system integration matters for a point-of-care reader because a result that stays on the device never reaches the laboratory record, the patient chart or the quality system. Connecting a reader means sending each result, with its identifiers and quality-control context, to a laboratory information system (LIS) or electronic health record (EHR) in a standard format.
OncoFirm™ is developing a research-stage prototype of a portable fluorescence reader. Connectivity is a design objective for that prototype. The interfaces described below are intentions to be specified and tested, not implemented or validated features.
Why reader results need to reach the LIS and EHR
Point-of-care instruments are often operated by staff outside the laboratory, away from the systems that track specimens and results. When results are copied by hand, three things are at risk: an accurate transcription, the link to the operator and reagent lot, and the ability to review quality control across devices.
The value of a near-patient result also depends on what happens next. Drain et al. (2014) argue that point-of-care tests improve outcomes only when the result feeds a clinical decision and a care pathway, and a result that is not recorded cannot do that. The wider setting is discussed in point-of-care testing in oncology.
Interoperability standards a reader interface must account for
| Standard | Maintained by | Role |
|---|---|---|
| HL7 Version 2 messaging | HL7 International | Event-based messages for orders and results; long established and widely deployed in laboratory systems |
| HL7 FHIR | HL7 International | Web-based resources such as Observation, DiagnosticReport, Specimen and Device, exchanged through an API |
| Instrument interface standards (originally ASTM, now CLSI) | Clinical and Laboratory Standards Institute | Low-level protocol and record format for the link between an analyzer and a host computer |
| Point-of-care connectivity standard (CLSI POCT01) | Clinical and Laboratory Standards Institute | Communication between point-of-care devices, a data manager and the LIS |
| LOINC and UCUM | Regenstrief Institute (LOINC); the UCUM Organization (UCUM) | Shared codes for the test performed and the units of the result |
Which standards apply depends on the site. A reader commonly reaches the LIS through middleware or a point-of-care data manager, not by a direct connection.
Data elements a point-of-care result message should carry
Whatever the transport, content matters more than format. A result that can be audited later needs at least the following.
- Patient or study-participant identifier, and the order or accession number where one exists.
- Test code (a LOINC code where one exists), result value, units, and a flag for invalid or out-of-range runs.
- Specimen type, collection time and time of measurement.
- Device identifier, strip or cartridge lot number and expiry date.
- Operator identifier.
- Quality-control and calibration status at the time of the run.
- Software and algorithm version, where software contributes to the result.
The last item is easy to overlook. If signal interpretation involves a model, the version that produced the result has to travel with it, for the reasons set out in AI in cancer diagnostics.
Security and audit considerations
A connected reader is a networked device that holds health information. The design objectives are familiar from other medical-device software: encryption of data in transit and at rest, authenticated users with role-based access, a tamper-evident audit trail, signed software updates and a documented process for handling vulnerabilities.
The privacy law that applies depends on the jurisdiction and on who operates the device. Hospital information-security teams set the requirements, so interface design has to start from their constraints and not from the device.
Research studies come before clinical integration
For a prototype, the first data destination is a study database, not a hospital LIS. In a research study, readings would be stored against coded participant identifiers under the study protocol and would not be returned to the clinical record. Building the data model around standard codes from the start avoids re-engineering later and makes multi-site data easier to pool.
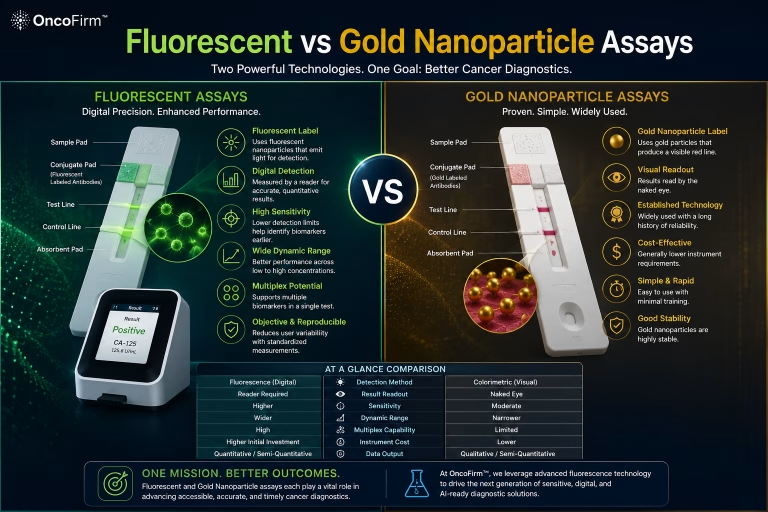
Raw signal data matter as much as final values. Retaining the underlying readings from the fluorescent lateral flow platform and the prototype digital reader would allow re-analysis as methods improve, a point developed in our framework for AI multi-biomarker blood tests.
Where informatics and laboratory partners fit
Open questions for OncoFirm’s planned grant projects include which message profile a first research interface should implement, how reader output should be mapped to standard codes while an assay is investigational, and how audit data should be structured for multi-site studies. Clinical laboratory informaticians, hospital point-of-care coordinators and middleware developers are the partners who can answer them.
Current questions are listed under research and development priorities, and joint work can be proposed through the collaboration opportunities page.
Frequently asked questions
What is the difference between an LIS and an EHR?
An LIS manages laboratory orders, specimens, results and quality control. An EHR is the patient’s clinical record, which receives results from the LIS along with data from other departments.
Does the OncoFirm reader connect to a laboratory information system today?
No. The reader is a research-stage prototype. LIS and EHR connectivity is a design objective that has not been implemented or validated.
What is a point-of-care data manager?
Software that sits between point-of-care devices and the LIS. It collects results, manages operators and quality-control rules, and forwards data in the format the LIS expects.
Related research and resources
- Digital diagnostic readers — the prototype reader and its design objectives.
- Rapid cancer diagnostic technologies — a map of assay and reader formats and their maturity.
- Discuss a grant opportunity — propose an informatics or interoperability study.
References and further reading
- HL7 International. HL7 Version 2 messaging standard.
- HL7 International. HL7 FHIR (Fast Healthcare Interoperability Resources) standard.
- Clinical and Laboratory Standards Institute. LIS01 and LIS02: standards for transferring information between clinical laboratory instruments and information systems (successors to ASTM E1381 and E1394).
- Clinical and Laboratory Standards Institute. POCT01: Point-of-care connectivity.
- Regenstrief Institute. LOINC: Logical Observation Identifiers Names and Codes.
- Drain PK, Hyle EP, Noubary F, et al. Diagnostic point-of-care tests in resource-limited settings. Lancet Infect Dis. 2014;14(3):239–249.
Research and regulatory status
OncoFirm™ technologies described on this site are in research and development. Their performance characteristics have not been established, and no OncoFirm product has been cleared, approved or authorized by the U.S. Food and Drug Administration. Nothing here is medical advice. Reference to a federal agency or funding program does not imply endorsement, funding, sponsorship or affiliation.